
Subscriber Benefit
As a subscriber you can listen to articles at work, in the car, or while you work out. Subscribe NowMore younger patients—think Gen Xers—are getting hip and knee replacements, accelerating a years-long trend of growth in joint replacement of patients under 65.
Many patients in their 50s simply want to end chronic joint pain from arthritis, injuries and years of wear and tear to get back to hiking or to take up pickleball.
For the health care industry, the wave of younger patients is helping to influence significant changes in treatments and even coverage of people with commercial insurance undergoing joint replacement.

“That was a life-changing moment having those two hips replaced,” said Melanie Lux, who had both hips replaced several months apart in 2019 at age 59.
Lux, a former Layfette resident who now lives in North Carolina, had lived an active life and ran marathons. But she broke her pelvis falling off a horse and said the pain made it difficult to even walk.
Now 65, Lux stays active, including hikes up to 5 miles.
Such outcomes have become common, although physicians and health insurers say younger patients should try other methods to address joint pain such as weight loss, anti-inflammatory medication and physical therapy before turning to surgery.
According to a study presented at the 2023 Annual Meeting of the American Academy of Orthopaedic Surgeons, about 28% of the 572,000 hip procedures performed annually in the United States are on patients under the age of 55.
That’s in part because improvements in surgical implants have extended the life of artificial joints to often past 20 years, making joint replacement more appealing to younger patients. In fact, a study presented at the 2023 annual meeting of the American Academy of Orthopaedic Surgeons looked at 5,153 patients age 65 and younger who had total hip arthroplasty, also called total hip replacement, and found that just 1% needed additional surgery within eight years.
Overall, patients 65 years or younger now make up 28% of all hip replacements, a number researchers have estimated could increase to 52% by 2030. And those under 65 could make up some 62% of total knee replacements, according to a study in Clinical Orthopaedics and Related Research that is more than a decade old but still widely cited by researchers.
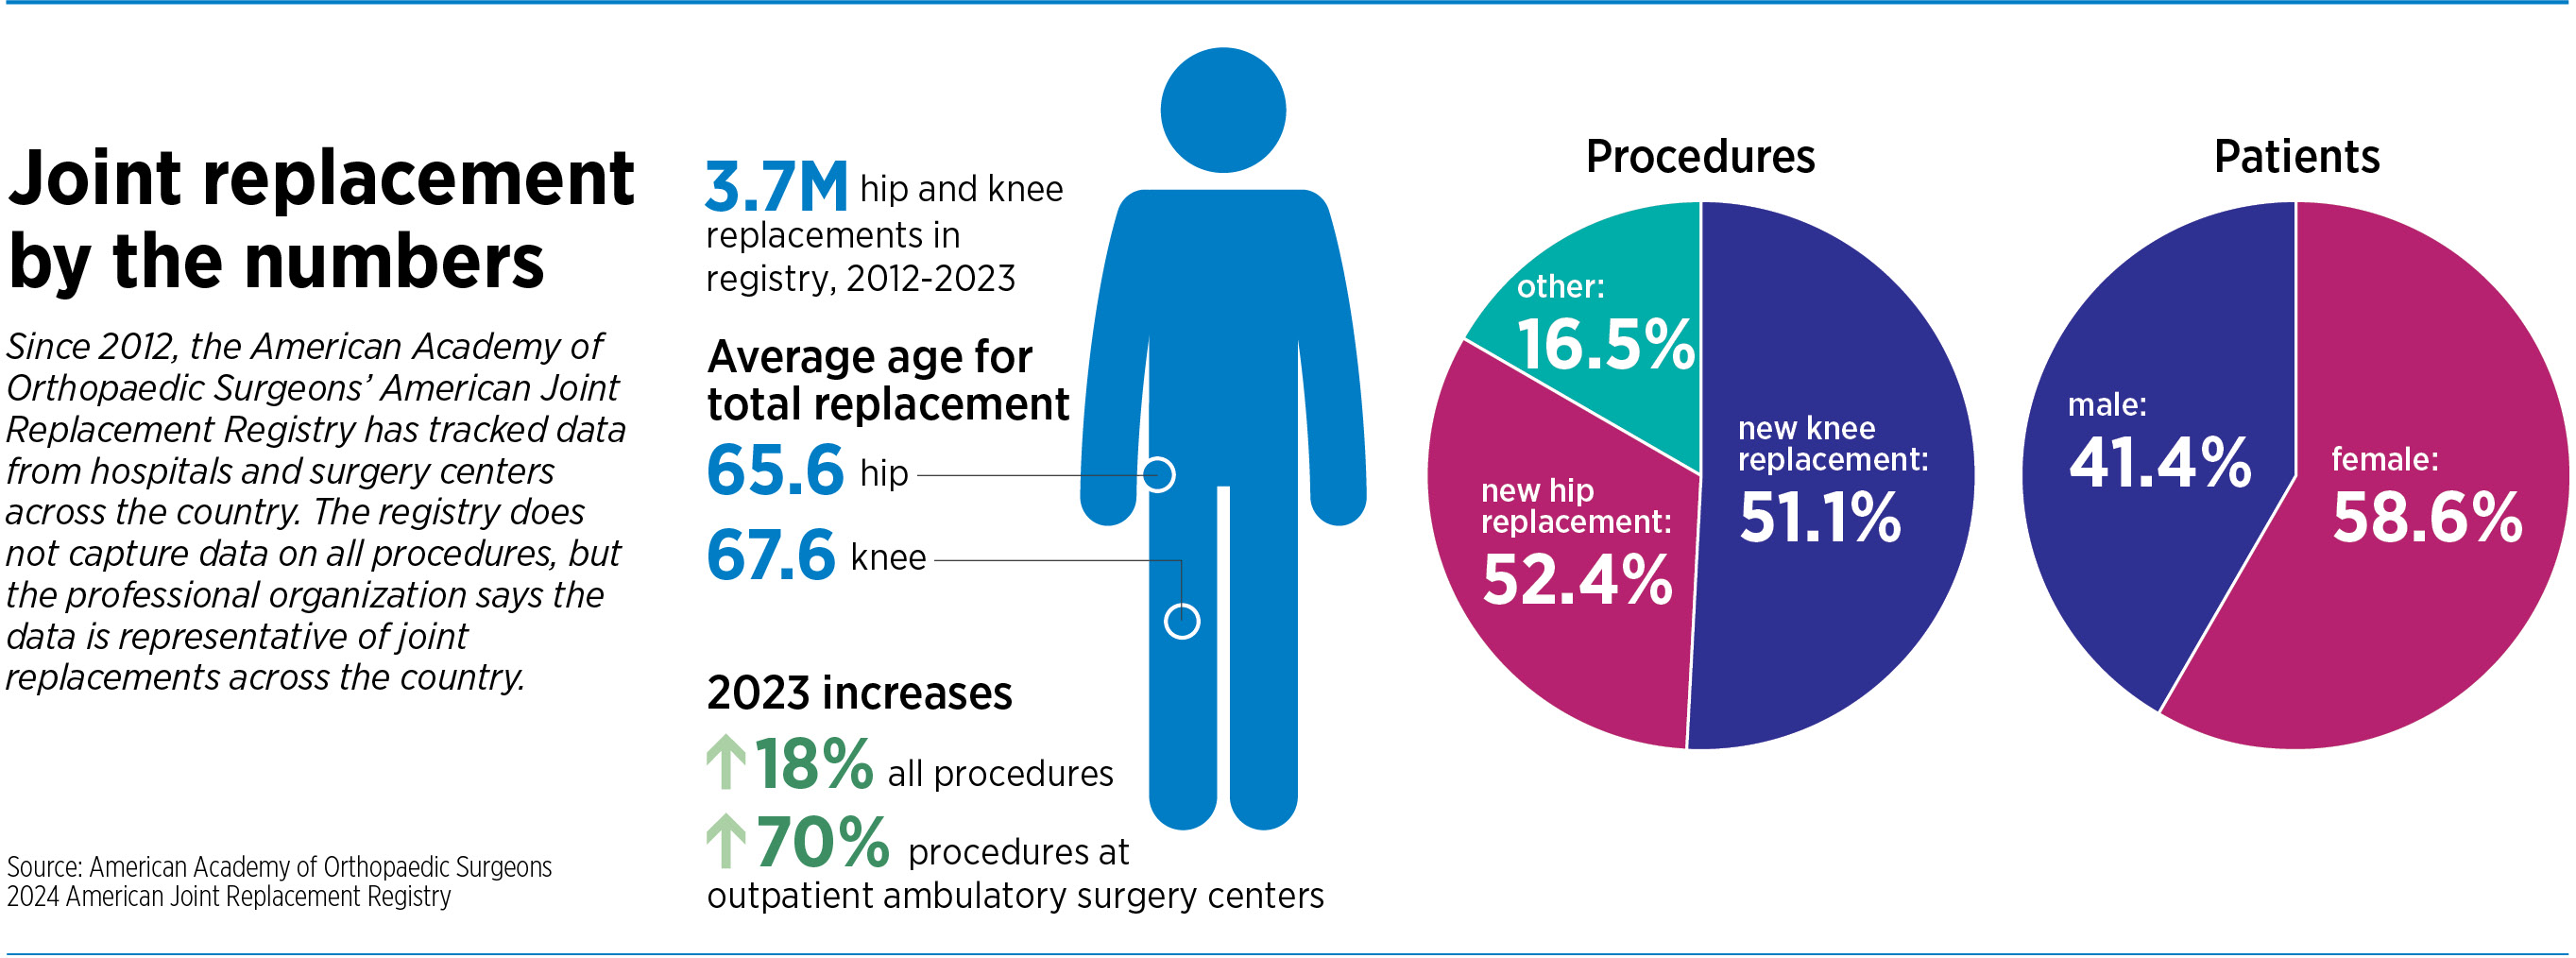
That growth comes as the procedures are up overall—about 18% in 2023 (the latest year for which statistics are available).
It’s easy to see that growth in central Indiana, where orthopedic facilities are opening, expanding and merging in an effort to attract patients and embrace different types of insurance agreements, such as direct-to-employer agreements for orthopedic coverage.
In January, OrthoIndy, Tri-State Orthopaedics in Evansville and Fort Wayne Orthopedics announced plans to merge and create OrthoIndiana. OrthoIndy says the merger is expected to be completed this year.
Then in February, the $35 million Indiana Orthopedic Institute opened as the first tenant at Noblesville’s Innovation Mile. The facility promotes concierge-level service for patients with a 38,000-square-foot building that includes an ambulatory surgery center with four operating rooms.
Differences by age

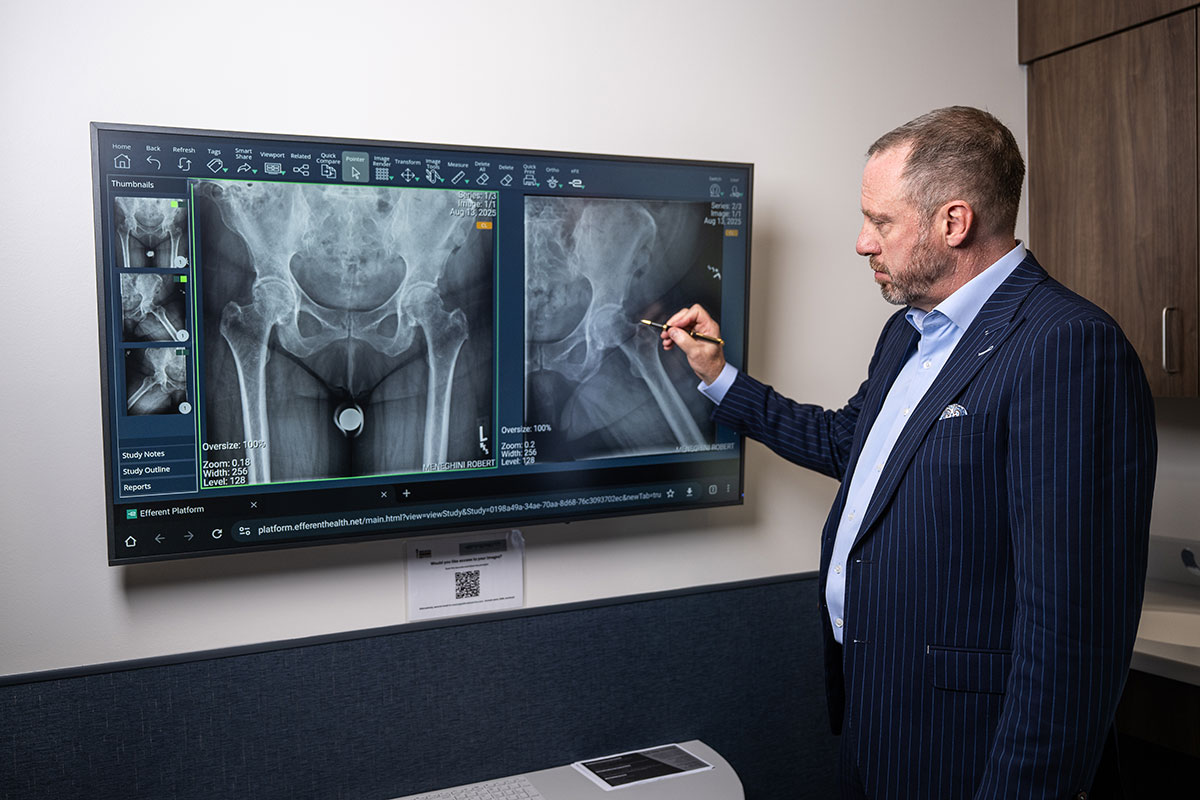
Dr. Michael Meneghini, CEO and founder of the Indiana Orthopedic Institute, calculates he’s done more than 10,000 hip and knee replacements over the past 20 years, and he’s noticed differences with patients under 65.
Those who are not yet retired facing joint replacement are more concerned about recovery time because of their work schedules.
Meneghini, who specializes in hip and knee replacements, said younger patients also increasingly want their joints replaced earlier than in the past.
“Thanks to our engineering advances and the technology, we now expect these implants to last 20 or 30 years,” he said. “People aren’t waiting anymore. They don’t need to be crippled.”
But treating younger patients can mean a different focus on costs. Those patients are more likely to be covered by workplace insurance programs—rather than Medicare—and might bear a larger share of the costs.
A complication-free hip replacement can cost $25,000, a huge expense for working-age patients and their employers that typically pay for most of their health care coverage.
Meneghini said the Indiana Orthopedic Institute, which has 13 orthopedic surgeons, looks for ways to reduce costs and lessen the need for additional care and hospitalization.
He said the institute has a value-based care team focused on direct-to-employer contracting, an increasingly popular arrangement in which employers contract with medical providers, bypassing traditional health insurance structures.
Meneghini said his organization is increasingly working toward a setup through which the Indiana Orthopedic Institute receives a set bundled fee for a procedure. That means if a patient requires additional care, the risk is on the provider.
Conversely, if the patient breezes through the procedure, the medical provider is rewarded with that same fee but lower costs.
“We’re going to own that 30-day risk, and if they get readmitted, it’s on us. We have to pay for them,” he said. “That’s where we’re evolving to.”
Managing the process
On the medical side, Meneghini said the Indiana Orthopedic Institute seeks to control the coordination of patient care from before to after surgery. For example, instead of sending patients outside the organization for pre-operative blood testing to ensure they are healthy for surgery, the institute does those tests in house.
That type of coordination can be more convenient for patients trying to balance work and home life with their health care.
“We know as surgeons exactly what you need to be safe during surgery,” said Meneghini, also president of the American Association of Hip and Knee Surgeons. “We put a program together, run by our anesthesiologists, which also are employed by us, and they run that clinic.”
He said the institute also works to reduce the chance of hospital stays. For example, patients need to be able to urinate after surgery to be discharged, which is sometimes a problem for men with enlarged prostates.
Meneghini said his group researched how to avoid certain medicines for pain and anesthesia that contribute to that problem.
In 2024, musculoskeletal procedures—with total hip and knee arthroplasty procedures as the top contributors—were a significant cost driver for employee-sponsored health coverage, according to a recent report from Indianapolis-based health analytics firm Springbuk.
Musculoskeletal procedures accounted for $7.83 of the $43.57 monthly increase per member of health insurance coverage, the single biggest contributor ahead of specialty prescriptions.
Total hip and knee arthroplasty procedures averaged more than $17,500 per claim, according to Springbuk’s Employee Health Trends 2025 Mid-year Update. The firm said the rate of procedures was stable from the year before, but costs were up about 10% for total hip replacement and 15% for total knee replacement.
Indianapolis-based Elevance Health’s Anthem Blue Cross and Blue Shield in Indiana said it has seen an increase in joint replacement procedures among adults under 60, as well as across the broader population.
Anthem spokesman Jeff Blunt said efforts to manage costs include addressing the roots of joint pain by promoting weight loss, smoking cessation and other healthy lifestyle practices.
When surgery is needed, Blunt said in an email, “We also work closely with providers to shift appropriate procedures to ambulatory surgery centers, where outcomes are often better and costs are lower.”
Anthem isn’t alone in its desire for procedures to be done at ambulatory surgery centers, where patients don’t stay overnight. Inpatient hip and knee replacements still outweigh those done as outpatient procedures, but in 2023 alone, 70% more procedures were done at outpatient ambulatory surgery centers than in the previous year.
Jumping through hoops

Even with the growth in less expensive, outpatient procedures, younger patients can face a longer approval process in getting joint replacement covered by commercial insurance than do patients covered by Medicare, according to Angie Stevenson, CEO of Forté Sports Medicine and Orthopedics
“Most of the commercial plans do offer coverage for this, but again, it’s the hoops that you have to go through,” she said.
Such scrutiny includes documenting that more conservative treatments and procedures did not work. Stevenson added that the prior authorization process can take two more weeks.
Forté performs more than 2,000 joint replacement surgeries a year on patients spanning from teenagers in rare cases to the elderly.

Dr. Lucian Warth, an orthopedic surgeon with Forté, estimated that at least half his joint replacement patients are under 65.
He said a series of surgical and implant innovations have allowed younger patients to get joint replacements earlier to improve their mobility and quality of life.
Major improvements include better methods to join the artificial joint to the bone to avoid loosening as well as to the bearing surfaces and how well the plastic and ceramic rub together over years.
The major shift, he said, has happened over the past 20 or 30 years. Before, patients who dropped hobbies like running but still could get by daily with less activity were often told to wait for surgery.
But Wath said younger patients don’t want to give up their favorite activities. They want to remain active, including in sports that used to be frowned on after hip or knee replacement surgeries. “These are things which are no longer a no-no in arthroplasty and joint replacement because of our trust of the biomaterials and the longevity,” Warth said.
Now, he said, patients “can kind of do whatever they want. I don’t recommend jumping out of an airplane, but I wouldn’t do that, anyways.”•
Please enable JavaScript to view this content.
Of course GenX is getting joint replacements; the oldest Xers are almost retirement age and might want to get the work done before they have to go on Medicare. (GenX cohort is now 45-60, birth years 1965-1980).
But the headline is a little misleading; the woman (Ms. Lux) featured in the story is not an Xer. She’s 65…a Boomer born in 1959/60.
I waited until I had Medicare because a $180 Part B deductible is a lot cheaper than my pre-Medicare $6000 deductible and $10,000 out-of-pocket max. Saw the surgeon 2 days after Medicare started, and got on the schedule.